
What is bempedoic acid?
Bempedoic acid is a cholesterol-lowering tablet taken once a day. It belongs to a newer class of medicines called ATP citrate lyase (ACL) inhibitors. It is not a statin.
High LDL cholesterol (medically, hypercholesterolaemia) is a major, modifiable cause of heart attack and stroke. The further LDL is lowered, and the longer it stays low, the lower the risk. For most people, a statin is the cornerstone of treatment, together with a healthy lifestyle.
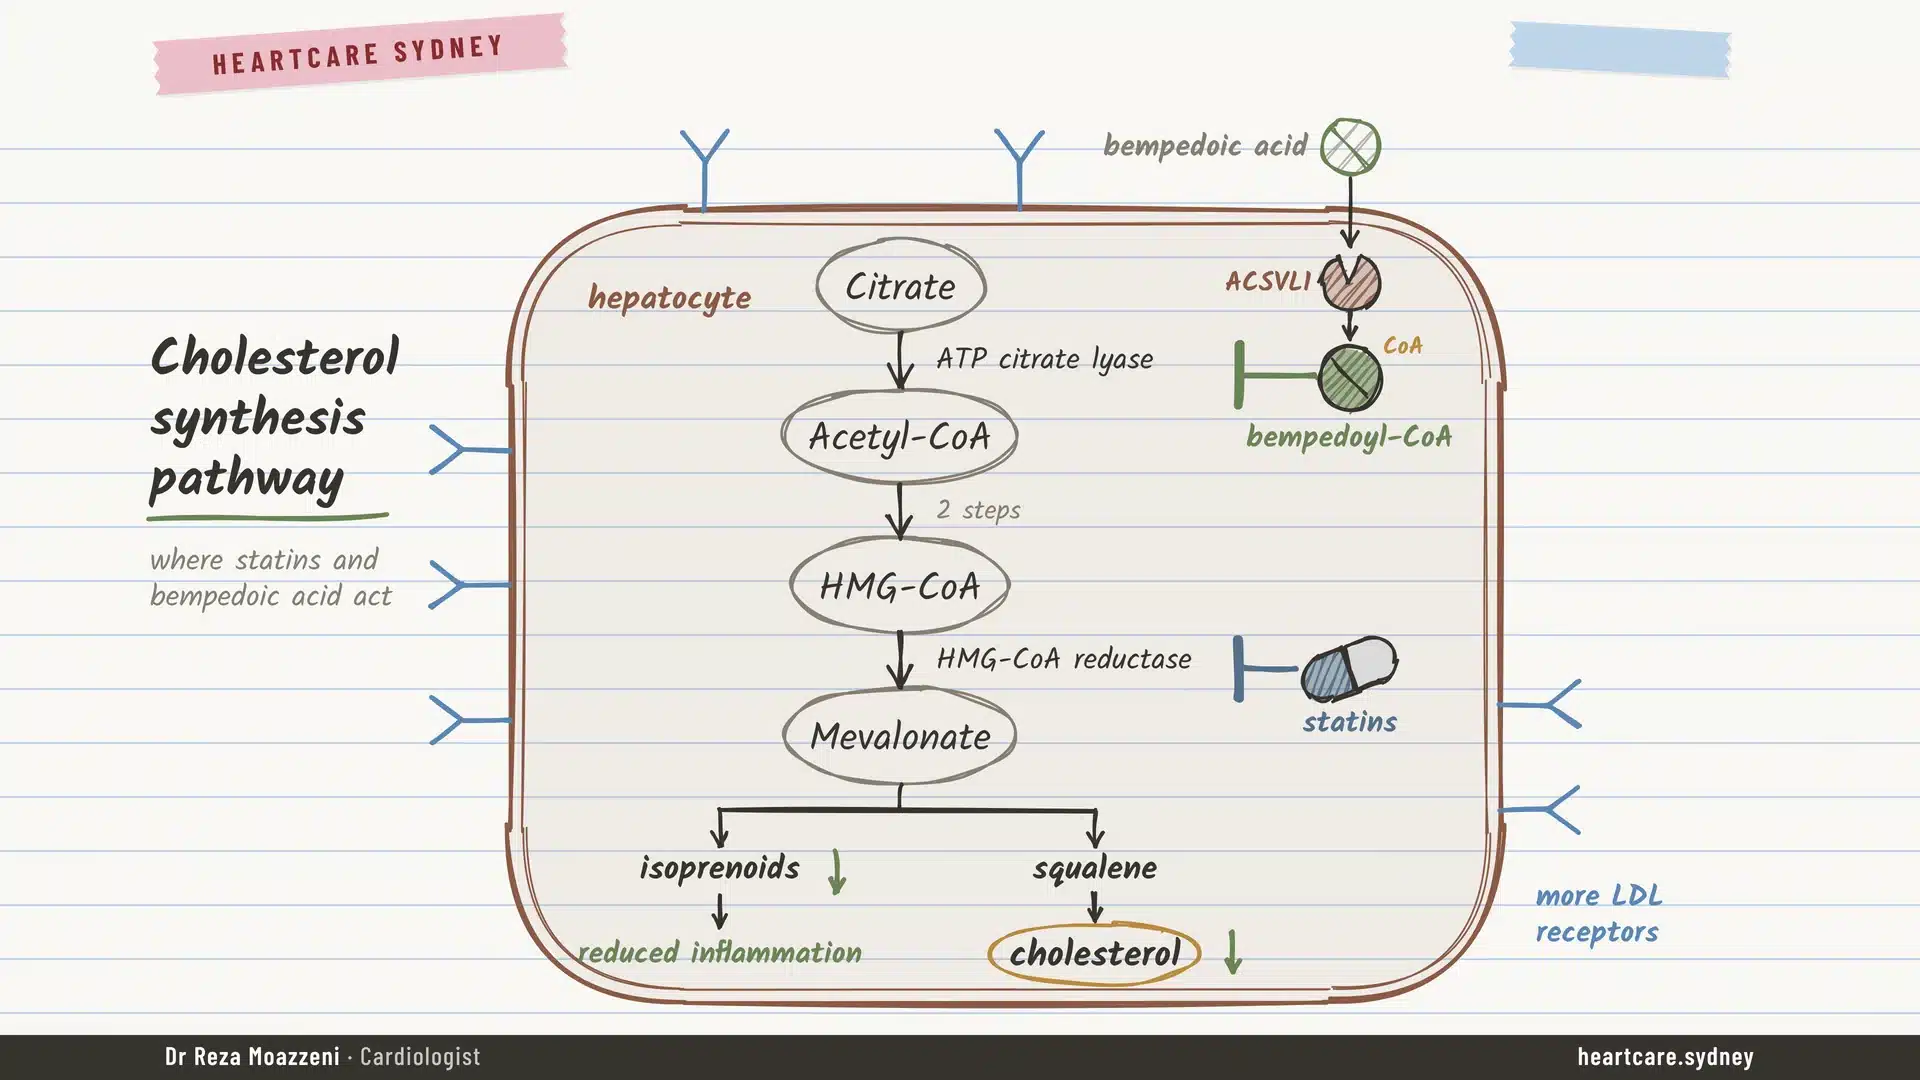
Like a statin, bempedoic acid reduces the amount of cholesterol the liver makes. The difference is where it acts: it is switched on in the liver but not in muscle. It was developed with people who have had muscle symptoms on statins in mind.
It comes on its own (Nexletol) or combined with ezetimibe in a single tablet (Nexlizet). Ezetimibe works in the gut by reducing cholesterol absorption, so the effects of the two drugs add together.
Prefer to watch? This video explains how bempedoic acid works, how it differs from statins, what the trial evidence shows and who it suits.
Bempedoic acid vs statins
Bempedoic acid has not been shown to be superior to statins. High-intensity statins generally lower LDL substantially more and remain the preferred starting treatment when tolerated.
| Question | Statin | Bempedoic acid |
|---|---|---|
| Treatment role | First choice for most people | Mainly for statin intolerance, or added when LDL remains above target |
| Evidence of fewer events | Decades of large trials, including fewer deaths | One large trial: fewer heart attacks and coronary procedures; no statistically significant reduction in deaths |
| Muscle pain | A common complaint, although in blinded trials often not caused by the statin | Not more frequent than placebo |
| Cost in Australia | PBS-subsidised, inexpensive | Not PBS-subsidised |
For each unit of LDL lowered, the reduction in major cardiovascular events appears similar to that seen with statins.3 This comes from an indirect comparison, not a head-to-head trial. It suggests that LDL lowering is what matters; it does not mean bempedoic acid is equivalent or superior to a statin.
When statins cause side effects
Muscle aches on a statin deserve proper assessment, because several causes are possible, including other medicines, an underactive thyroid and unaccustomed exercise. Some people stopped statins because of muscle symptoms and were then tested in blinded trials. In those trials, symptoms were reported about as often on placebo as on the statin (the nocebo effect). That does not mean the symptoms are imagined. It means the cause is often not the statin itself.
Many people who stopped one statin can take a different statin, a lower dose or less frequent dosing. It helps to distinguish partial intolerance (some statin can be taken) from complete intolerance, because the next step differs. Repeated unsuccessful statin trials are not the only route to effective treatment. Non-statin options with outcome evidence exist.
Who might benefit from bempedoic acid?
Bempedoic acid is usually considered for people at high cardiovascular risk whose LDL remains above target, and who:
- cannot take a statin because of side effects, or can only take a low dose; or
- still need further LDL lowering despite the highest statin dose they tolerate, often with ezetimibe; or
- have familial hypercholesterolaemia and need several medicines to reach target.
Some people prefer not to take a statin, and that is worth discussing. The trial evidence, however, comes from people who had side effects on statins, not from people who switched away from a statin they tolerated.
How treatment may be chosen
- Cardiovascular risk and the LDL target are reviewed. For selected people without established heart disease, where the treatment decision is uncertain, a coronary calcium score can help refine risk.
- The tolerated statin and dose are established. This is often a different statin or a lower dose.
- Ezetimibe is commonly added. It is PBS-listed and inexpensive, and it lowers LDL by a further 20–25% when added to a statin.
- If more lowering is needed, the options include bempedoic acid (not PBS-subsidised) or an injectable treatment such as evolocumab. The choice depends on how far LDL still needs to fall, eligibility for PBS subsidy, and cost.
This is a flexible approach, not a fixed rule. The 2026 ACC/AHA dyslipidaemia guideline includes bempedoic acid among its recommended non-statin options, chosen according to cardiovascular risk, tolerance and the additional LDL reduction required.7
Bempedoic acid is not used during pregnancy or breastfeeding. It needs more discussion before starting in people with a history of gout or tendon problems, and in anyone who could become pregnant.
How much does bempedoic acid lower LDL cholesterol?
| Treatment | Typical LDL reduction |
|---|---|
| High-intensity statin | 50% or more |
| Moderate-intensity statin | 30–49% |
| Ezetimibe alone | About 15–20% |
| Ezetimibe added to a statin | A further 20–25% |
| Bempedoic acid, with no statin or a low-dose statin | About 20–25% |
| Bempedoic acid added to a statin | A further 15–20% |
| Bempedoic acid with ezetimibe (combined tablet) | About 35–40% (both drugs together) |
These figures are approximate and come from different trials. The combination figure is the effect of both drugs together, not an extra 35–40% after ezetimibe has already been started.
A worked example: a 20% reduction takes an LDL of 4.0 mmol/L (155 mg/dL) to about 3.2 mmol/L (124 mg/dL). That is worthwhile. People with established heart disease, however, usually have targets well below 2 mmol/L, so bempedoic acid is often one part of a combination. (Need to convert units? Use the cholesterol unit converter.)
The effect is seen within weeks. A repeat cholesterol test is usually done 8–12 weeks after starting.
Does bempedoic acid prevent heart attacks and strokes?
The main evidence is the CLEAR Outcomes trial.1 It enrolled 13,970 people from 32 countries who were unable or unwilling to take guideline-recommended statin doses because of side effects, and who had heart disease or were at high risk of it. Most took no statin; a very low statin dose was allowed. Participants were randomised to bempedoic acid or placebo and followed for a median of 3.4 years. Average LDL at the start was 3.6 mmol/L (139 mg/dL), and bempedoic acid lowered it by 0.75 mmol/L (29 mg/dL) more than placebo, a 21% difference.
Approximately 63 people would need treatment for about 3.4 years to prevent one first major cardiovascular event. This is an average from the trial, not a prediction for any one person.
| Outcome | Placebo | Bempedoic acid | Result |
|---|---|---|---|
| Combined major cardiovascular events | 13.3% | 11.7% | 13% lower (significant) |
| Heart attack (fatal or non-fatal) | 4.8% | 3.7% | 23% lower (significant) |
| Coronary stent or bypass | 7.6% | 6.2% | 19% lower (significant) |
| Stroke | — | — | No significant difference |
| Cardiovascular death and death from any cause | — | — | No significant difference |
Relative reductions are calculated from the reported hazard ratios.
The benefit came mainly from fewer heart attacks and fewer coronary procedures. The trial did not demonstrate a statistically significant reduction in cardiovascular death or death from any cause during follow-up. As with any preventive treatment, the absolute benefit depends on starting risk: the higher the risk, the larger the benefit.
People without previous heart disease
About 4,200 participants had no previous heart attack or stroke but were at high risk, for example through diabetes at an older age or a coronary calcium score above 400. In this group, major events occurred in 5.3% on bempedoic acid versus 7.6% on placebo, about 23 fewer per 1,000.2 This is a subgroup of one trial in carefully selected high-risk people. It does not show that the drug works better in primary prevention.
What has not yet been tested
CLEAR Outcomes tested bempedoic acid mainly in people taking little or no statin. There is no outcomes trial of bempedoic acid added to a standard statin dose. In that setting, the LDL-lowering effect is well established and guidelines support selected use. The reduction in events, however, is inferred from the LDL reduction rather than measured directly.
How does bempedoic acid work?
It works in three steps:
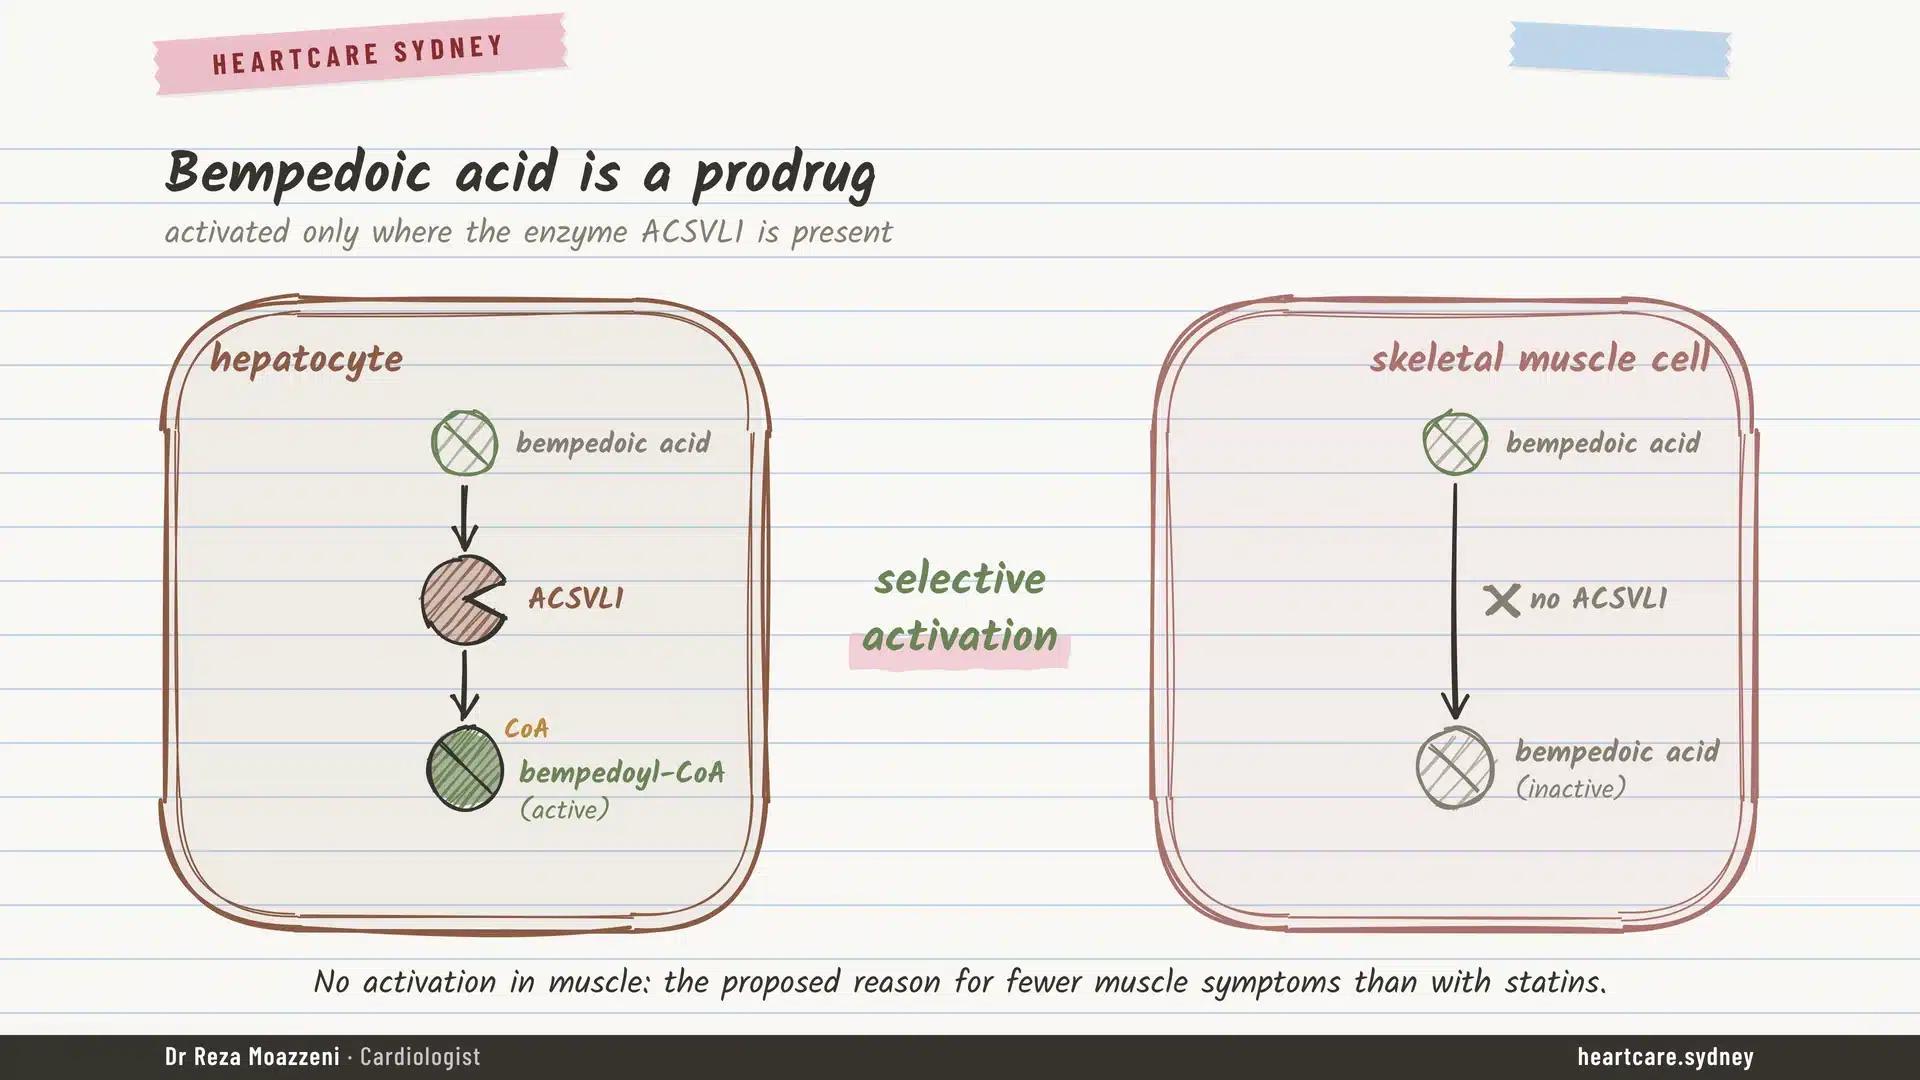
- The tablet is absorbed and activated mainly in the liver, by an enzyme called ACSVL1.
- Once active, it blocks ATP citrate lyase (ACL). This enzyme sits upstream of HMG-CoA reductase (the enzyme statins block) on the same cholesterol-making pathway.
- With less cholesterol being made, liver cells add more LDL receptors to their surface and clear more LDL from the blood.
Why muscle is largely spared
Skeletal muscle lacks ACSVL1, so bempedoic acid stays inactive there. This gives a biological reason to expect fewer muscle side effects, and in CLEAR Outcomes muscle pain was not more frequent than with placebo. It does not guarantee that muscle symptoms cannot occur.
Side effects, interactions and monitoring
Most people tolerate bempedoic acid well. These are the effects to know about:
| Topic | What to know |
|---|---|
| Uric acid and gout | Uric acid rises in many people, often within the first month. In CLEAR Outcomes, gout occurred in about 3 in 100 people on bempedoic acid versus 2 in 100 on placebo. A history of gout should be discussed before starting. If gout develops, your doctor may stop the medicine. |
| Gallstones | Slightly more common: about 2 in 100 versus 1 in 100. |
| Muscle symptoms | Muscle pain was not more frequent than placebo. Muscle spasms were slightly more common: about 4 in 100 versus 3 in 100. |
| Tendon injury | Uncommon, but a recognised warning. Risk is higher over age 60, with corticosteroids or fluoroquinolone antibiotics, with kidney failure, or after previous tendon problems. |
| Blood tests | Small rises in creatinine (kidney test) and liver enzymes, and a small fall in haemoglobin, can occur. |
| Pregnancy and breastfeeding | Do not use during pregnancy or while breastfeeding. Discuss pregnancy plans and contraception with your doctor before starting. It should be stopped before trying to conceive, or as soon as pregnancy is recognised. |
Medicines that interact
Bempedoic acid raises blood levels of simvastatin and pravastatin. In Australia, simvastatin is usually limited to 20 mg a day when taken with bempedoic acid; 40 mg is used only in selected high-risk patients, and higher doses must not be combined with it.8 Your doctor may also review other cholesterol medicines, such as pravastatin or a fibrate. Bring a full list of your medicines to your appointment.
Taking it and follow-up
The dose is one 180 mg tablet daily, with or without food. Liver function is checked before starting. A cholesterol test is usually repeated 8–12 weeks after starting, with uric acid, kidney, liver and blood count tests as your doctor advises. Ask your pharmacist for the Consumer Medicine Information (CMI) leaflet for the Australian product.
Frequently asked questions
Is bempedoic acid a statin?
No. It blocks a different enzyme, earlier in the same cholesterol-making pathway, and it is not activated in muscle.
Is it better than atorvastatin or rosuvastatin?
It has not been shown to be superior. High-intensity statins generally lower LDL substantially more and remain the preferred starting treatment when tolerated.
Can I stop my statin and take this instead?
Not without discussing it with your doctor. Switching usually means less LDL lowering. Bempedoic acid is mainly for people who cannot take an effective statin dose, or as an add-on.
Can I take it with a statin or ezetimibe?
Yes. It is often combined with both. Nexlizet contains bempedoic acid and ezetimibe in one tablet. Simvastatin and pravastatin doses may need adjusting.
Can it cause muscle pain?
In CLEAR Outcomes, muscle pain was not more frequent than with placebo, although muscle spasms were slightly more common. Tell your doctor about any new muscle symptoms.
Can it cause gout?
It raises uric acid, and gout was slightly more common in the main trial: about 3 in 100 people versus 2 in 100 on placebo.
Does it increase diabetes risk?
No increase was seen. In CLEAR Outcomes, new diabetes developed in 11.1% on bempedoic acid and 11.5% on placebo.5 A diabetes-prevention benefit has not been demonstrated.
Is it available on the PBS?
No, as at October 2026. Ask your pharmacist about current availability and private cost.
How soon will I need another cholesterol test?
Usually 8–12 weeks after starting.
Do I still need to watch my diet and exercise?
Yes. A healthy diet, regular activity and not smoking add to the benefit of any cholesterol medicine. See how to prevent a heart attack.
Evidence for clinicians
Detailed trial data for health professionals. Select a heading to expand it.
CLEAR lipid trials: placebo-corrected LDL-C change at week 12
| Trial | Population | n | LDL-C vs placebo |
|---|---|---|---|
| CLEAR Harmony (Ray, NEJM 2019) | ASCVD/HeFH on maximally tolerated statin | 2,230 | −18.1% |
| CLEAR Wisdom (Goldberg, JAMA 2019) | ASCVD/HeFH on maximally tolerated LLT | 779 | −17.4% |
| CLEAR Serenity (Laufs, JAHA 2019) | Intolerant of ≥2 statins | 345 | −21.4% |
| CLEAR Tranquility (Ballantyne, Atherosclerosis 2018) | Statin intolerant, background ezetimibe | 269 | −28.5% |
| BA/EZE FDC (Ballantyne, EJPC 2020) | High risk, maximally tolerated statin | 382 randomised; 301 in primary analysis | −38.0% (FDC) |
In CLEAR Serenity, myalgia occurred in 4.7% on bempedoic acid versus 7.2% on placebo.
CLEAR Outcomes (Nissen, NEJM 2023): main results
n = 13,970 patients unable or unwilling to take guideline-recommended statins because of adverse effects; median follow-up 40.6 months. Baseline LDL-C 3.6 mmol/L (139 mg/dL); placebo-corrected reduction at 6 months 0.75 mmol/L (29.2 mg/dL; 21.1%). hsCRP fell about 22% versus placebo.1
- MACE-4: 11.7% vs 13.3%; HR 0.87 (95% CI 0.79–0.96)
- MACE-3: 8.2% vs 9.5%; HR 0.85 (0.76–0.96)
- Fatal/non-fatal MI: 3.7% vs 4.8%; HR 0.77 (0.66–0.91)
- Coronary revascularisation: HR 0.81
- Stroke: not significant. CV death and all-cause death (prespecified secondary endpoints): no significant difference
- More frequent on bempedoic acid: gout (3.1% vs 2.1%), cholelithiasis (2.2% vs 1.2%), muscle spasms (4% vs 3%), anaemia (4.7% vs 3.9%), and small rises in creatinine, uric acid and hepatic enzymes
Consistency with statin trials
Using CTT methodology, the HR for major vascular events normalised per 1 mmol/L LDL-C reduction was 0.75 (0.63–0.90), compared with a rate ratio of 0.78 for statins.3 This is an indirect comparison. It supports LDL lowering as the principal mechanism and does not establish equivalence or superiority.
Prespecified and subgroup analyses
- Primary prevention (Nissen, JAMA 2023): n = 4,206; MACE-4 5.3% vs 7.6%; HR 0.70 (0.55–0.89). Enrolment required high risk, for example diabetes with age criteria or CAC above 400.2
- Total events (Nicholls, JAMA Cardiol 2024): first plus recurrent MACE-4 reduced by 20%, compared with 13% for first events.4
- Diabetes (Ray, Lancet Diabetes Endocrinol 2024): MACE-4 HR 0.83 in patients with diabetes (ARR 2.4%). New-onset diabetes 11.1% vs 11.5% (HR 0.95, 0.83–1.09).5
- PAD (Bonaca, Circulation 2026): 1,624 patients with PAD. First major adverse limb events reduced by 36%; total MALE by 45% (RR 0.55, 0.35–0.85). Subgroup analysis.6
- hsCRP: relative benefit was similar across baseline hsCRP strata. Whether the hsCRP reduction contributes benefit beyond LDL lowering is unknown.
Evidence gap: add-on to statin therapy
There is no outcomes trial on a background of standard or high-intensity statin therapy. Add-on use rests on LDL-C efficacy, CTT-consistent benefit per mmol/L and guideline endorsement.
Prescribing points (Australian PI)
- Pregnancy and breastfeeding: contraindicated. Advise effective contraception; discontinue before conception, or when pregnancy is planned or recognised.
- Simvastatin: usually limit to 20 mg daily. 40 mg only in narrowly defined high-risk circumstances where benefit outweighs risk (see PI); doses above 40 mg are contraindicated.
- Liver: check liver function at initiation; discontinue for persistent transaminase elevation above 3 × ULN.
- Gout: discontinue if hyperuricaemia is accompanied by symptoms of gout.
Source: Australian Product Information, sections 4.2–4.6.8
Also in the US label (for comparison): avoid pravastatin above 40 mg; with fibrates, check triglycerides and HDL-C four weeks after starting the combination; discontinue immediately if tendon rupture occurs and consider discontinuing for joint pain, swelling or inflammation.11
PBAC decision, July 2026
The PBAC did not recommend listing for patients who are statin intolerant or on a maximally tolerated statin and remain above the LDL-C threshold despite ezetimibe. It considered that the CLEAR Outcomes population did not adequately reflect the proposed listing population, making the size of benefit uncertain. It also judged the economic model to be substantially uncertain, and considered that a price reduction plus a risk-sharing arrangement was likely needed. It acknowledged a clinical need, particularly for patients not eligible for PCSK9 inhibitors.9
References & further reading
Clinical references
- Nissen SE, et al. Bempedoic acid and cardiovascular outcomes in statin-intolerant patients. N Engl J Med 2023;388:1353–64.
- Nissen SE, et al. Bempedoic acid for primary prevention of cardiovascular events in statin-intolerant patients. JAMA 2023;330:131–40.
- Lincoff AM, et al. Comparative cardiovascular benefits of bempedoic acid and statin drugs. J Am Coll Cardiol 2024;84:152–62.
- Nicholls SJ, et al. Impact of bempedoic acid on total cardiovascular events. JAMA Cardiol 2024;9:245–53.
- Ray KK, et al. Efficacy and safety of bempedoic acid among patients with and without diabetes. Lancet Diabetes Endocrinol 2024;12:19–28.
- Bonaca MP, et al. Bempedoic acid and first and recurrent limb outcomes in statin-intolerant patients with peripheral artery disease. Circulation 2026;154:966–75.
- 2026 ACC/AHA multisociety guideline on the management of dyslipidemia. Circulation 2026.
- Nexletol (bempedoic acid) Australian Product Information. Seqirus; linked from the ARTG record.
- PBS Medicine Status: bempedoic acid; bempedoic acid with ezetimibe. Current at 1 October 2026.
- Therapeutic Goods Administration. Australian Register of Therapeutic Goods: Nexletol (ARTG 501108) and Nexlizet (ARTG 501110).
- Nexletol (bempedoic acid) prescribing information (US), revised January 2026.
Further reading for patients
Reviewing your cholesterol treatment
Statin side effects, or an LDL that stays above target despite treatment, are good reasons for a specialist review. The review covers your cardiovascular risk, what you can tolerate and which combination of treatments suits you. Consultations are available in English and Persian (Farsi) at Westmead and St Leonards. A GP referral is required.
Book a consultationRelated reading
2026 ACC/AHA dyslipidaemia guideline
LDL targets and where non-statin treatments fit.
Severe hyperlipidaemia: a stepwise approach
How very high cholesterol is assessed and treated.
Cardiovascular risk calculators
Estimate risk with PREVENT, MESA and calcium score tools.