
Most heart attacks are linked to things that can be measured and changed: blood pressure, cholesterol, smoking, blood sugar, activity and diet. The most effective plan is to know your risk, treat high blood pressure and cholesterol (with medication if needed), stop smoking, move most days and eat a Mediterranean-style diet. A good first step is a Heart Health Check with your GP.
Call Triple Zero (000) immediately. Warning signs include chest pain, pressure or discomfort (which may spread to the arm, neck, jaw or back), breathlessness, sweating, nausea or dizziness. Symptoms vary — don't wait for severe chest pain.
The 5 steps to lower your heart attack risk
Step 1 — Knowing your risk
Why it matters. Your risk comes from several factors together. Slightly high cholesterol alone may mean low risk; add smoking and diabetes and it can mean high risk. Your overall risk shows how much treatment is worthwhile.
What to do
- Ask your GP for a Heart Health Check. A Medicare rebate may be available for eligible adults aged 30 and over, once every 12 months.2
- For people without known cardiovascular disease, Australian guidelines recommend a full risk assessment from age 45 to 79, from 35 for people with diabetes, and from 30 for Aboriginal and Torres Strait Islander people.1
- Your GP uses the Australian risk calculator (Aus CVD Risk) to estimate your chance of a heart attack, stroke or related event over the next 5 years: low (under 5%), intermediate (5% to under 10%) or high (10% or more).1
- Some people are at high risk without a calculator — including people with familial hypercholesterolaemia (FH), an inherited condition that causes very high cholesterol from birth, and people with moderate-to-severe kidney disease.
- Tell your doctor about things the calculator can miss:1
- a parent, brother or sister with heart disease or stroke at a young age (a man under 55 or a woman under 65)
- South Asian background, including Indian, Pakistani, Sri Lankan, Bangladeshi and Nepali
- high blood pressure, pre-eclampsia or diabetes during a pregnancy
- kidney disease, even if mild
- very high cholesterol in you or your family — check your FH score
- Ask about a lipoprotein(a) test. Lp(a) is an inherited cholesterol particle that diet and exercise barely change, so one test in adulthood is usually enough.3 A high result means your other risk factors deserve tighter control.
This week: Book a Heart Health Check and ask: “What is my 5-year risk?”
Step 2 — Treating blood pressure, cholesterol and blood sugar
Why it matters. High blood pressure, cholesterol and blood sugar damage arteries silently for years — and they're among the most treatable risks. In trials, every 1 mmol/L drop in LDL cholesterol cut major cardiovascular events by about 22%,4 and every 10 mmHg fall in systolic blood pressure (the top number) by about 20%.5 These are relative reductions from different studies and can't be added together.
Medication is part of prevention, not a sign of failure. Healthy habits lower blood pressure and cholesterol, but often not by enough when risk is high or the cause is inherited. The two work together.
Blood pressure
- One clinic reading can mislead: readings can rise at the doctor's (“white-coat” effect) or be normal there but high at home. A week of home readings gives a truer picture — morning and evening for 7 days, two readings a minute apart each time, averaged without day 1. A home average of 135/85 or higher is generally considered high. See how to measure blood pressure correctly at home.
- Many people need more than one medicine to reach their target. Side effects can usually be fixed by changing the dose or the medicine — talk to your doctor rather than stopping.
Keeping track of your readings. Health Diary is currently free and runs in your phone's browser. Record readings, see your 7- and 30-day averages, and print a report for your doctor. Recording a reading doesn't notify anyone — your diary stays private until you share it. It also has a blood sugar diary and a medication list.
Cholesterol
- LDL cholesterol (the “bad” cholesterol) builds plaque. Both the level and how long it stays high matter, and your target depends on your overall risk.
- Diet usually lowers LDL modestly. Statins lower it substantially and reduce heart attacks and strokes; ezetimibe or a PCSK9 inhibitor (an injection) can be added if needed.
- Side effects? Tell your doctor. In blinded trials, most muscle aches reported on statins weren't caused by the statin,6 and there are usually other options. More in our 2026 cholesterol guideline summary.
Blood sugar
- Type 2 diabetes roughly doubles the risk of a heart attack.
- HbA1c is a blood test of your average blood sugar over about 3 months. At 6.0–6.4% (42–46 mmol/mol), diabetes risk is higher — and lifestyle changes can delay or prevent it.19
- With diabetes, some newer medicines (SGLT2 inhibitors and GLP-1 receptor agonists) also protect the heart and kidneys. Ask whether one suits you.
This week: Start a 7-day home blood pressure record. If you take medicines, check you're taking them as prescribed.
Step 3 — Stopping smoking
Why it matters. Smoking damages the artery lining, makes blood clot more easily and raises blood pressure. Risk falls once you quit: in the Framingham Heart Study, heavy smokers who quit had 39% lower cardiovascular risk within 5 years than those who kept smoking.7
Cutting down helps much less than you'd expect. One cigarette a day still carries a third to a half of the extra heart disease risk of 20 a day.8 The goal is to stop completely.
What helps
- Support plus medicine works best. Support: Quitline 13 7848, your GP or pharmacist. Medicine: nicotine replacement (a patch plus gum, lozenge or spray) or varenicline.
- Nicotine vapes worked better than nicotine replacement in trials.9 In Australia they're pharmacy-only and a second option when first-line treatments haven't worked. Long-term safety isn't known, so aim to stop vaping too, in time.
This week: Set a quit date and call Quitline (13 7848), or talk to your GP or pharmacist.
Step 4 — Moving more
Why it matters. Regular activity lowers blood pressure, improves cholesterol and blood sugar, and helps with weight. The biggest gain comes from going from very little activity to some.
Australia's 24-hour movement guidelines (2026) recommend, for all adults:10
- 30 minutes or more of moderate-to-vigorous activity on most days — brisk walking counts
- muscle-strengthening activities on 2 or more days a week
- activities for balance, mobility and coordination on 3 or more days a week
- several hours of light activity across the day, breaking up long periods of sitting as often as you can
Getting started
- If you've been inactive, start with 10-minute walks and add a few minutes each week.
- If you get chest discomfort, unusual breathlessness, dizziness or palpitations during exercise, stop. If you think it could be a heart attack, call 000 straight away. If the symptoms settle quickly, see your doctor before exercising again.

This week: Add a 10–20 minute brisk walk to your day — after a meal is an easy time.
Step 5 — Eating well, sleeping well and managing stress
Food
The best-supported pattern is Mediterranean-style eating: vegetables, fruit, legumes, wholegrains, olive oil, nuts and fish, with less processed meat, sugary drinks and ultra-processed food. In the PREDIMED trial, high-risk adults eating this way had about 30% fewer major cardiovascular events (relative; mostly fewer strokes) than those on a reduced-fat diet.11
| Instead of | Try |
|---|---|
| Butter, ghee, coconut oil | Olive oil, canola oil or an unsaturated spread |
| Processed meats (bacon, salami, ham) | Fish, chicken, legumes or eggs |
| White bread and white rice | Wholegrain bread, brown rice, oats, barley |
| Sugary drinks and juice | Water, sparkling water, unsweetened tea or coffee |
| Chips, biscuits and pastries | Unsalted nuts, fruit or plain yoghurt |
| Salty takeaway and packet sauces | Home cooking with herbs, spices, lemon and garlic |
Less salt lowers blood pressure. With alcohol, less is better for the heart: Australian guidelines advise no more than 10 standard drinks a week and no more than 4 on any day (more in alcohol and heart health). High triglycerides? See how to lower triglycerides.
Weight
If you carry extra weight, losing 5–10% of your body weight improves blood pressure, blood sugar and cholesterol. Fat around the waist carries more risk than fat elsewhere.
Sleep
Aim for 7–9 hours a night (7–8 for older adults), with regular bed and wake times.10 Loud snoring, gasping or pauses in breathing at night, or daytime sleepiness, can be signs of obstructive sleep apnoea, which raises blood pressure and is treatable — ask your GP.
Stress
Long-term stress can raise blood pressure, disturb sleep and make healthy habits harder to keep. Regular activity, time with people you're close to, enough sleep and professional support when stress feels overwhelming all help.
This week: Make one swap from the table, and set a regular bedtime.
Your heart numbers at a glance
These are general guides. Your own targets depend on your overall risk and whether you already have heart disease; your doctor will set them with you.
Blood pressure
- What it means: below 120/80 is ideal. 140/90 or higher in the clinic, or a home average of 135/85 or higher, is high.
- What to do next: if it's high, confirm with home readings. If treated, your target is set with your doctor — often below 130/80 if tolerated.
- How often: at least every 2 years if normal; more often if raised.
LDL cholesterol
- What it means: there's no single “normal” — the right level depends on your overall risk.
- What to do next: ask what your target is. Common goals are below 2.6, 1.8 or 1.4 mmol/L (100, 70 or 55 mg/dL) as risk rises.*3 Find your LDL target
- How often: with your risk assessment; again a few weeks to a few months after starting or changing treatment.
Lipoprotein(a)
- What it means: inherited, and risk rises progressively. 125 nmol/L or above — or 50 mg/dL or above if your laboratory reports in mg/dL — is generally regarded as high.3 These are thresholds in two different units, not a conversion.
- What to do next: not a target to chase. A high result means tighter control of everything else.
- How often: once in adulthood.
HbA1c (average blood sugar)
- What it means: 6.0–6.4% (42–46 mmol/mol) means a higher risk of diabetes. 6.5% (48 mmol/mol) or above suggests diabetes, usually confirmed with a repeat test.19
- What to do next: at 6.0–6.4%, lifestyle changes and a repeat test in a year.19 With diabetes, a target — often around 7% (53 mmol/mol) — set individually.
- How often: as advised; every 3–6 months if you have diabetes.
Waist
- What it means: risk rises from 94 cm in men and 80 cm in women (lower cut-offs apply for some Asian backgrounds). A useful but imperfect guide.
- What to do next: even modest weight loss improves blood pressure, blood sugar and cholesterol.
* LDL goals are from the 2026 US (ACC/AHA) guideline, which uses 10-year risk categories. These don't map directly onto the Australian 5-year categories — your doctor will set your target.
Your doctor may also check apolipoprotein B (apoB), which helps estimate the number of particles that can contribute to plaque — useful in some situations, such as high triglycerides or diabetes. More about apoB.
How a heart attack happens
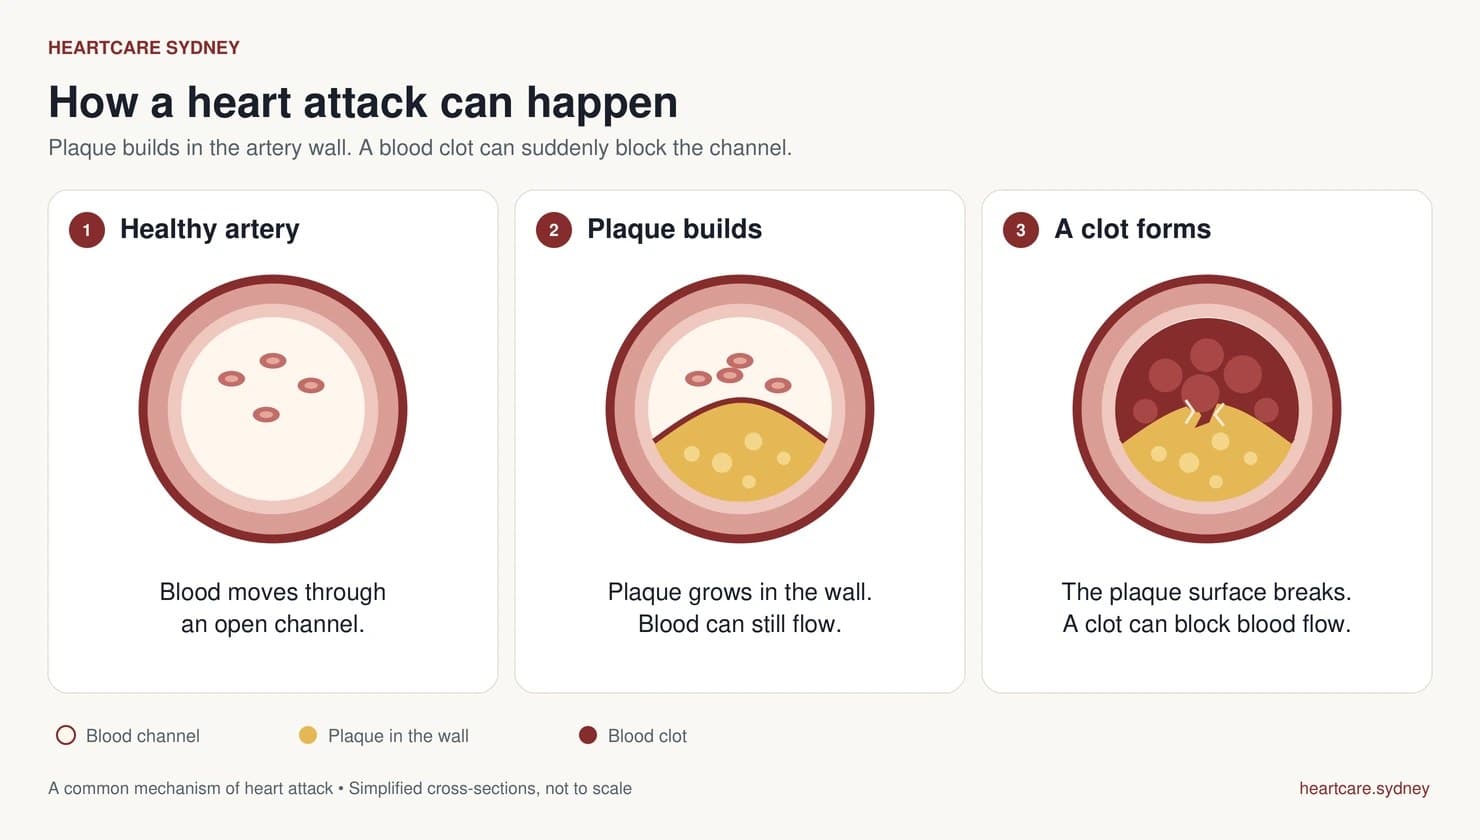
A heart attack usually starts with plaque — a build-up of cholesterol, inflammatory cells and scar tissue inside the wall of a coronary artery. Plaque grows slowly, often over decades, without symptoms. Most heart attacks happen when the surface of a plaque cracks or wears away and a blood clot forms on top, blocking blood flow to part of the heart. The plaque that triggers a heart attack is often not the one narrowing the artery most.
How much is preventable? In INTERHEART (about 30,000 people, 52 countries), nine common factors — including smoking, cholesterol, blood pressure, diabetes, waist size, stress, diet and activity — were linked to about 90% of the population risk of a first heart attack.12 That's a population figure, not a personal promise.
Why do fit, healthy people still have heart attacks?
Fitness and healthy arteries aren't the same thing.
- Plaque reflects a lifetime of cholesterol, blood pressure and past smoking. Getting fit at 50 lowers future risk but doesn't remove plaque already there.
- Inherited conditions such as FH or high Lp(a) can raise risk despite healthy habits. Lifestyle still helps, but medication may also be needed.
- Fit people often blame chest tightness or breathlessness on being “out of shape” and delay seeing a doctor.
- Hard exertion can briefly raise heart attack risk in someone who already has plaque — much less so in people who exercise regularly, so build up gradually.
Do I need a statin if I exercise and eat well?
Possibly. It depends on your overall risk, your LDL and inherited factors — not on how healthy your lifestyle is. Lifestyle usually lowers LDL modestly; if your risk is high, a statin adds protection lifestyle alone can't, and your habits add their own benefit.
What heart tests can — and can't — tell you
Tests are most useful when they answer a specific question, such as “Would a calcium score change whether I start a statin?” They refine your risk; they don't lower it.
Coronary calcium score (CT, no contrast)
- Useful for: refining risk when it's borderline or intermediate and the statin decision is uncertain.
- Can't tell you: a zero doesn't rule out soft (non-calcified) plaque; not a test for symptoms.
Stress test (exercise ECG or stress echo)
- Useful for: investigating symptoms such as chest pain or breathlessness on exertion.
- Can't tell you: a normal result doesn't rule out plaque or guarantee against a future heart attack.
Echocardiogram
- Useful for: heart muscle, valves and pumping function; investigating symptoms, a murmur or an abnormal ECG.
- Can't tell you: doesn't show the coronary arteries or plaque.
CT coronary angiogram
- Useful for: looking directly at the coronary arteries in people with symptoms or in selected situations.
- Can't tell you: uses contrast and radiation; not a routine screening test.
Does a calcium score of zero mean I have no heart disease?
Zero means no calcified plaque was seen. Risk over the next several years is usually low, and some people at borderline risk can reasonably delay a statin. But zero doesn't rule out soft, non-calcified plaque, which is more common in younger people and smokers. Australian guidance advises caution if you smoke, have diabetes or a strong family history.13 More in our guide to the coronary calcium score.
A calcium score is for people without symptoms. A zero is reassuring about risk — not a reason to ignore new chest pain or breathlessness.
Can a normal stress test miss heart disease?
Yes. A stress test looks for narrowings severe enough to reduce blood flow during exercise, but many heart attacks start in plaque that isn't yet narrowing the artery that much. A normal result is good news about blood flow now and usually means low short-term risk — not proof that there's no plaque. Keep treating your risk factors, and see your doctor if symptoms return or change. See how a stress echocardiogram works.
Already had a heart attack, stent or bypass?
If you already have coronary heart disease, the aim is to prevent another event. The same five steps apply, alongside the treatment prescribed for you.
- Medicines are central. Cholesterol-lowering medicines, blood pressure tablets and antiplatelet medicines (which help stop clots forming, such as aspirin) lower the risk of another heart attack. Keep taking them when you feel well, and don't stop any without talking to your cardiologist.
- LDL targets are lower — many people with established heart disease aim for below 1.4 mmol/L (55 mg/dL).3
- Cardiac rehabilitation is recommended after a heart attack, stent or bypass. Ask for a referral if you haven't been offered one.
- Medicines and healthy habits remain essential after a stent or bypass. Many people with stable coronary disease can start with medical treatment. Procedures can relieve angina (chest discomfort from reduced blood flow), and some people need them because of their artery anatomy, symptoms or reduced heart function.14,15
My heart prevention plan
Use this before and after your appointment. The printable version has space to write each answer in — fill it in with your doctor and keep it with your medication list.
Bring
- All your medicines and supplements, with doses (Health Diary medication list)
- Home blood pressure readings — ideally 7 days (Health Diary report or the printable diary)
- Recent blood tests, especially cholesterol, HbA1c and kidney function
- Family history: who had heart disease, stroke or sudden death, and at what age
- Pregnancy history if relevant: high blood pressure, pre-eclampsia or diabetes
- Smoking or vaping history
- Any symptoms with exertion — when they happen and how long they last
Questions to ask
- What is my 5-year cardiovascular risk?
- What should my blood pressure and LDL targets be?
- Should I have my Lp(a) checked?
- Would a calcium score change my treatment?
My plan
- My 5-year cardiovascular risk (if applicable)
- My blood pressure target
- My LDL target (mmol/L)
- My medicines for prevention
- One habit I'll change first
- Next review — when, and with whom
Download the printable plan (PDF)
Three common myths, in 76 seconds
Read the video text
3 heart prevention myths, explained. Fitness. Tests. Medication. Small steps. A personal plan. Know your risk.
Myth 1 — fitness: “I'm fit, so my arteries are clear.” Fitness helps, but inherited risk still matters: cholesterol over a lifetime, family history, and lipoprotein(a), or Lp(a). Plaque can be silent.
Myth 2 — tests: “A normal stress test means I'm protected.” A stress test checks blood supply under stress. A normal result does not rule out all plaque or guarantee future protection. Keep treating your risk factors.
Myth 3 — medication: “Needing medication means I've failed.” Healthy habits and medication can work together: move regularly, eat well, and treat your risk.
Your next step: start with a Heart Health Check. Ask your GP: “What is my risk?” Know your risk. Treat blood pressure and cholesterol. Stop smoking. Move most days. Eat well and protect your sleep.
Know when to act. Possible heart attack? Call 000 immediately. Warning signs can include chest discomfort, breathlessness, sweating, nausea or dizziness. Symptoms vary. Do not wait for severe chest pain.
Common questions
Is it ever too late to start?
No. Quitting smoking, lowering blood pressure and moving more help at any age. Statins can help older people too: in the Australian STAREE trial, adults aged 70 and over without heart disease, diabetes or dementia who took atorvastatin had 30% fewer major cardiovascular events (a relative reduction) over about 6 years — 6.0% compared with 8.3%. The trial did not show a significant improvement in survival free of dementia or persistent physical disability.16 Age alone isn't a reason to avoid a statin; the decision weighs your health, frailty, other medicines and preferences.
Should I take aspirin to prevent a heart attack?
After a heart attack or stent, an antiplatelet medicine such as aspirin is usually part of treatment. After a stroke, it depends on the type and cause: many people whose stroke was caused by a blocked artery (an ischaemic stroke) take an antiplatelet, while a stroke linked to atrial fibrillation usually needs an anticoagulant (blood thinner) instead. Without a heart attack or stroke, aspirin isn't routinely recommended — the small benefit is largely offset by bleeding risk, and US guidance advises against starting it for prevention from age 60.17 Don't start aspirin on your own.
Are statins safe long term?
For most people, yes. In large blinded trials, more than 90% of muscle symptoms reported by people on statins weren't caused by the statin.6 Statins slightly raise blood sugar, mostly in people already near the diabetes threshold; for those who need a statin, the heart benefit outweighs this. Serious liver injury is rare, and trials haven't shown effects on memory.
What about supplements — fish oil, CoQ10, garlic, vitamin D?
Over-the-counter supplements haven't shown consistent benefits for preventing cardiovascular disease, and they shouldn't replace prescribed treatment or healthy habits. A high-dose prescription omega-3 (icosapent ethyl) helped selected people with high triglycerides, but it's a different product from ordinary fish oil. Eating fish twice a week is supported.
Do weight-loss injections prevent heart attacks?
In the SELECT trial, adults with overweight or obesity and established cardiovascular disease, without diabetes, who took semaglutide had a 20% lower combined risk of cardiovascular death, non-fatal heart attack or non-fatal stroke (a relative reduction: 6.5% compared with 8.0% over about 3 years).18 That result applies to semaglutide in that group — it isn't evidence for every weight-loss injection, or for people without established cardiovascular disease. These medicines work alongside the other steps, not instead of treating blood pressure and cholesterol.
What about coffee, eggs and red meat?
For most healthy adults, up to 3–4 cups of coffee a day is fine. Around one egg a day doesn't meaningfully raise heart risk for most people. Processed meat (bacon, sausages, ham, salami) is consistently linked with higher risk — keep it occasional, and keep unprocessed red meat modest.
Can stress cause a heart attack?
Sudden severe stress can trigger a heart attack in someone who already has plaque. It can also cause takotsubo (“broken heart”) syndrome, which mimics a heart attack without blocked arteries. Long-term stress works mainly through blood pressure, poor sleep and habits.
When should I see a cardiologist?
Start with your GP. A referral makes sense for chest pain or unexplained breathlessness, a strong family history of early heart disease, very high LDL or high Lp(a), an abnormal ECG or echocardiogram, blood pressure that stays high despite treatment, or a calcium score that's high for your age. A referral is needed for a Medicare rebate.
Updated 13 October 2026. Steps reordered to put risk assessment and treatment first; figures updated to current evidence and Australian guidance; new sections on why fit people have heart attacks, what tests can and can't show, and a printable prevention plan.
References and further reading
Clinical references
- Nelson MR, Banks E, et al. 2023 Australian guideline for assessing and managing cardiovascular disease risk. Med J Aust. 2024;220(9):482–90. DOI
- Medicare Benefits Schedule. Item 699 — Heart health assessment. MBS Online
- 2026 ACC/AHA/Multisociety Guideline on the Management of Dyslipidemia. J Am Coll Cardiol / Circulation. March 2026. Our summary
- Cholesterol Treatment Trialists' (CTT) Collaboration. Efficacy and safety of more intensive lowering of LDL cholesterol: a meta-analysis of data from 170,000 participants in 26 randomised trials. Lancet. 2010;376:1670–81. DOI
- Ettehad D, et al. Blood pressure lowering for prevention of cardiovascular disease and death: a systematic review and meta-analysis. Lancet. 2016;387:957–67. DOI
- Cholesterol Treatment Trialists' (CTT) Collaboration. Effect of statin therapy on muscle symptoms: an individual participant data meta-analysis of large-scale, randomised, double-blind trials. Lancet. 2022;400:832–45. PubMed
- Duncan MS, et al. Association of smoking cessation with subsequent risk of cardiovascular disease. JAMA. 2019;322:642–50. PubMed
- Hackshaw A, et al. Low cigarette consumption and risk of coronary heart disease and stroke: meta-analysis of 141 cohort studies in 55 study reports. BMJ. 2018;360:j5855. DOI
- Lindson N, et al. Electronic cigarettes for smoking cessation. Cochrane Database Syst Rev. 2026, Issue 8. CD010216. Cochrane
- Australian Government Department of Health, Disability and Ageing. Australian 24-hour movement guidelines for adults (18–64 years) and older adults (65+ years). 2026. health.gov.au
- Estruch R, et al. Primary prevention of cardiovascular disease with a Mediterranean diet supplemented with extra-virgin olive oil or nuts (PREDIMED). N Engl J Med. 2018;378:e34. PubMed
- Yusuf S, et al. Effect of potentially modifiable risk factors associated with myocardial infarction in 52 countries (the INTERHEART study). Lancet. 2004;364:937–52. PubMed
- National Heart Foundation of Australia. Position statement on coronary artery calcium scoring for the primary prevention of cardiovascular disease in Australia. Med J Aust. 2021;214(9). PMC
- Maron DJ, et al. Initial invasive or conservative strategy for stable coronary disease (ISCHEMIA). N Engl J Med. 2020;382:1395–1407. PubMed
- Boden WE, et al. Optimal medical therapy with or without PCI for stable coronary disease (COURAGE). N Engl J Med. 2007;356:1503–16. PubMed
- Zoungas S, Wolfe R, Moran C, et al. Atorvastatin, cardiovascular events, and disability-free survival in older adults (STAREE). N Engl J Med. 2026. ESC summary
- US Preventive Services Task Force. Aspirin use to prevent cardiovascular disease. JAMA. 2022;327:1577–84. DOI
- Lincoff AM, et al. Semaglutide and cardiovascular outcomes in obesity without diabetes (SELECT). N Engl J Med. 2023;389:2221–32. DOI
- Royal Australian College of General Practitioners. Management of type 2 diabetes: a handbook for general practice. Melbourne: RACGP; 2020. RACGP
Further reading for patients
- Heart Foundation — Heart attack warning signs
- Heart Foundation — Heart Health Checks
- Health Diary — How to measure blood pressure correctly at home
Get a personalised prevention plan
If you'd like to turn this guide into a plan that fits you — your risk calculation, cholesterol and Lp(a) results, blood pressure review and, where it would change treatment, a calcium score — book a preventive cardiology consultation. A referral is needed for a Medicare rebate.